Showing posts with label mumps. Show all posts

Thursday, December 18, 2014

Mumps on ice

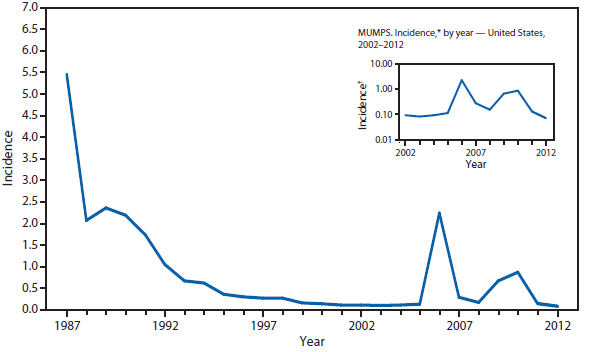
This figure is a line graph that presents the incidence per 100,000 population of mumps cases in the United States from 1987 to 2012The mumps vaccine was licensed in the US in 1967 and recommendations regarding use of the vaccine have varied since its introduction. As described in the CDC Manual for the Surveillance of Vaccine-Preventable Diseases, the Advisory Committee on Immunization Practices (ACIP)
made an official recommendation for one dose of mumps vaccine for all children at any age after 12 months in 1977. In 1989, children began receiving two doses of mumps vaccine because of the implementation of a two-dose measles vaccination policy using the combined measles, mumps, and rubella vaccine (MMR) vaccine. In 2006, a two-dose mumps vaccine policy was recommended for school-aged children, students at post high school educational institutions, healthcare personnel, and international travelers.
Mumps vaccine has had a profound impact on the annual incidence of mumps in the US. In 1968 more than 152,000 cases reported, while in 2003 only 231 cases were reported. Recently, however, the nation has witnessed a resurgence of the disease, and an apparently ongoing outbreak of mumps in the National Hockey League (NHL) illustrates how the mumps virus continues to circulate in the general population. The NHL outbreak has, so far, affected 15 players on five teams, and another three cases are suspected. A timeline of events surrounding the cases suggests the outbreak originated in October.

Doni Bloomfield wrote an article this week (which also contains "mumps on ice" in the title) that, in one vivid passage, illustrates potential infection pathways for mumps virus in professional hockey. Bloomfield quotes James Conway of the University of Wisconsin School of Medicine and Public Health:
You watch these guys taking a big hit up against the boards, there’s snot and boogers and all sorts of stuff flying around as the guy gets hit hard enough, so I don’t think it would surprise me at all that there’s some transmission just by stuff flying around during the games. It’s a sloppy, messy sport.
That's colorful imagery for sure, but in addition to how, it's important to ask why this and other recent outbreaks are occurring. Mumps is, after all, a vaccine preventable disease. 

It's possible that this group of players belongs to a demographic that has lower vaccine coverage, potentially due to parental reticence to vaccinate. However, at least one player is known to have had two doses of vaccine: one childhood dose, consistent with ACIP guidelines in the late 1980s, and another in preparation for foreign travel in February of 2014. Tara Haelle wrote an article recently on the mumps vaccine in which she quotes Paul Offit discussing the rate of waning immunity associated with this vaccine. Offit notes that
If you look at the three [MMR component] vaccines, measles and rubella induce larger memory in B and T cells . . . They have longer lasting immunity. Mumps is the weak sister of the three. You start to see vulnerability 10 years after the first dose and 10 years after the second dose.
Waning vaccine-associated immunity could thus play a role in this outbreak, and in potential future ones as well. Boosters have been used to compensate for waning immunity in past mumps outbreaks. Might a third dose of vaccine be appropriate for the general population at some point in the future?

(image source: CDC)

Wednesday, April 16, 2014

Measles, right here in River City

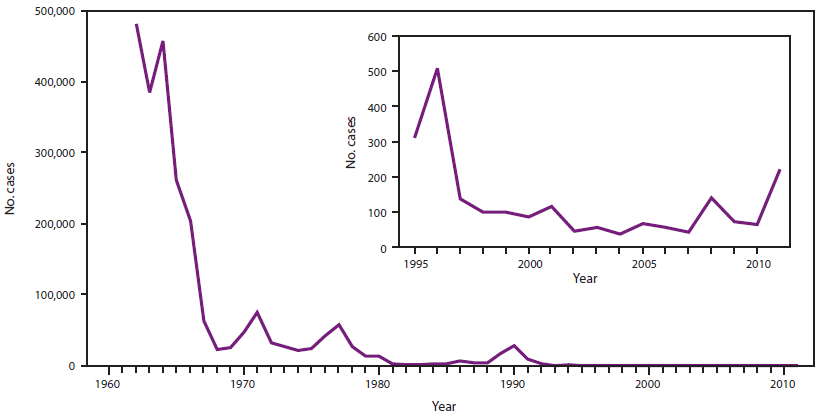
File:Measles Aztec drawing.jpgMeasles used to be a major childhood disease, affecting virtually all children in dramatic periodic outbreaks. The measles virus causes high fever, rash, runny nose, conjunctivitis, and malaise. It can also result in death. In the 1960s a vaccine was developed, and it was ultimately merged into what became the currently-used MMR vaccine. That vaccine helped reduce the incidence of measles to virtually non-existent levels in the US. A recent MMWR depicts the dramatic decrease of disease after vaccine introduction:

This figure provides the number of measles cases in the United States from 1962 through 2011. After the introduction of the 1-dose measles vaccination program, the number of reported measles cases decreased during the late 1960s and early 1970s to approximately 22,000-75,000 cases per year.

Sadly, a 1998 report finding an association between the MMR vaccine and autism led to decrease in the incidence of vaccination and attendant increase in measles disease (inset of the graphic). That study was retracted in 2010 after investigators failed to confirm its findings. Nonetheless, a large number of consumers continue to believe the bogus result that the MMR and other vaccines cause autism and thus forgo vaccinating their children. (There are additional reasons people do not vaccinate their children besides fear of autism; just google "why I'm not vaccinating my child" and you'll get a good sampling of those reasons.)

Recent months have seen continued transmission of measles in susceptible populations across the US, including California and New York City. Why is measles a problem when an effective vaccine is so commonly available? Often, travelers become infected overseas in areas where the prevalence of the measles virus is higher than in the US, and transmit the virus to susceptible individuals (often children) when they return. In NYC, a substantial proportion of the cases appear to be in children too young for the vaccine.

The simple fact is that if people do not have immunity to measles, they are overwhelmingly likely to develop infection and disease following an exposure. This is a highly transmissible virus; estimates of the basic reproduction number, R0, are as high as 18. The high degree of herd immunity in the US limits the size of outbreaks, but, as we see in the current situations in New York and California, transmission occurs due to the presence of unvaccinated persons.

The figure shows the number of U.S residents with measles who were unvaccinated (n = 117), by reasons for not receiving measles vaccine in the United States during January 1-July 13, 2013. Of the 117 who were unvaccinated, 92 (79%) had philosophical objections to vaccination, six (5%) had missed opportunities for vaccination, 15 (13%) occurred among infants aged <12 months who were not eligible for vaccination, and for four (3%) persons the reason for no vaccination was unknown.In the US, all states require children to be vaccinated before starting school. However, depending on the state, children can be exempted from the requirement for medical (notably in transplant patients and those with allergies to vaccine components), religious, or personal belief reasons. Figure 3 (shown here) of a recent MMWR on measles transmission in the US depicts the current reasons for not receiving measles vaccination. Between January and August 2013, most measles cases (82%) were in persons who were unvaccinated. Of those, 79% cited philosophical/religious objections to vaccination as the reason for not receiving the vaccine. Outbreaks related to religious communities are well documented in the news; recent examples include measles in Washington State and British Columbia, measles in New York City, and measles in Texas.

Though this post has focused measles, there are similar issues with other vaccine preventable diseases, including mumps, pertussis, meningitis, and others. Vaccine coverage, both in the US and overseas, must be increased if we are to decrease the incidence of such diseases. We must learn how to more effectively communicate the benefits and risks to those who decide against vaccination.

(image source: first graphic, Wikipedia; second & third graphics, CDC)